Rheumatoid Arthritis
An autoimmune condition in which the immune system attacks the lining of the joints — causing pain, swelling and stiffness. With early diagnosis and the right treatment, most people can control it and protect their joints for the long term.
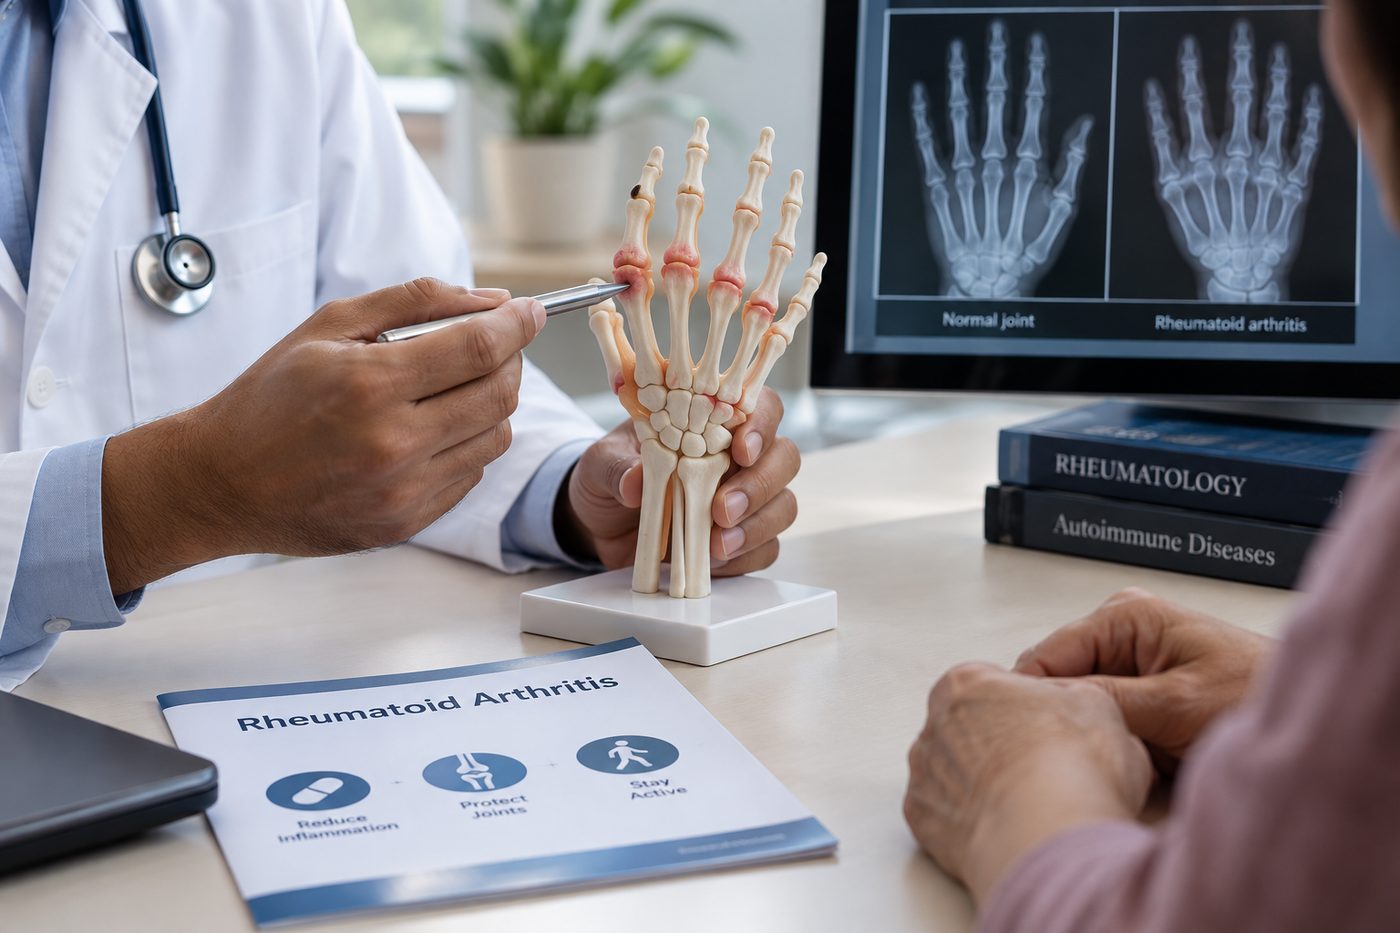
What is rheumatoid arthritis?
Rheumatoid arthritis is a chronic inflammatory disease. Unlike the "wear and tear" of osteoarthritis, RA is driven by the immune system mistakenly targeting the synovium — the soft tissue that lines your joints. This causes ongoing inflammation that, if left untreated, can gradually damage cartilage and bone.
RA usually affects the small joints of the hands, wrists and feet first, and characteristically affects the same joints on both sides of the body. It can also affect larger joints and, in some people, other organs. It is more common in women and often begins between the ages of 30 and 60, though it can occur at any age.
Symptoms to recognise
RA often begins gradually. The most common early signs include:
- Swollen, tender joints — most often the fingers, wrists and feet, usually on both sides
- Morning stiffness that lasts more than 30–60 minutes and eases as the day goes on
- Joints that feel warm and look puffy or red
- Fatigue, a general feeling of being unwell, and sometimes a low-grade fever
- Symptoms that come and go in "flares" but tend to persist and spread over time
What causes it?
The exact cause of RA is not fully known, but it results from a combination of genetic tendency and environmental triggers that set off an abnormal immune response. Smoking is a well-established risk factor and can make the disease more aggressive. A family history of RA or other autoimmune conditions can also increase risk. Importantly, RA is not caused by diet or lifestyle alone, and it is not contagious.
When should you see a rheumatologist?
See a rheumatologist if you have joint pain and swelling lasting more than a few weeks, prolonged morning stiffness, or symptoms affecting both sides of the body. Early referral matters — a rheumatologist can confirm the diagnosis and begin treatment before joint damage sets in. Many patients spend months being treated for general aches before the underlying RA is identified; seeing a specialist sooner changes the long-term outcome.
How it is diagnosed
There is no single test for RA. Diagnosis brings together your symptoms, a clinical examination, blood tests and, where helpful, imaging such as musculoskeletal ultrasound — which can reveal inflammation that isn't obvious on examination.
- Blood tests — rheumatoid factor (RF), anti-CCP antibodies, and inflammation markers (ESR, CRP)
- Clinical examination — assessing which joints are swollen and tender, and the overall pattern
- Imaging — ultrasound or X-rays to detect inflammation and assess the joints
How it is treated
RA is very treatable. The goal of modern treatment is remission or low disease activity — meaning little or no inflammation, so you can live normally and your joints are protected. Treatment is tailored to each person and typically includes:
- Disease-modifying drugs (DMARDs) such as methotrexate — the cornerstone of treatment, acting on the underlying disease rather than just the pain
- Biologic and targeted therapies for people whose disease needs more than conventional DMARDs
- Short-term anti-inflammatories or steroids to settle flares while long-term treatment takes effect
- Regular monitoring — adjusting treatment over time based on response, with periodic blood tests
With today's treatments, the outlook for RA is far better than even a decade ago. Most people diagnosed early and treated consistently stay active and prevent serious joint damage.
Concerned about joint pain or swelling?
If these symptoms sound familiar, a specialist assessment is the right next step. Consultations are held as a walk-in OPD — no appointment needed.
Clinic timings & location